

Yes, you can sue for ER malpractice in Georgia, but the bar sits far higher than in a standard negligence case. Under O.C.G.A. § 51-1-29.5, you must prove gross negligence by clear and convincing evidence, not the ordinary “reasonable care” standard used elsewhere in personal injury law. Add a two-year filing deadline and a maximum five-year statute of ultimate repose, and the window to act correctly is narrower than most patients realize.
TL;DR:
- Georgia law requires proving gross negligence by clear and convincing evidence, making ER malpractice claims significantly more difficult than standard negligence cases.
- Only injuries occurring during the “bona fide emergency” period are covered, and once a patient is stabilized or admitted, ordinary negligence rules may apply instead.
- Filing deadlines are strict, with a two-year statute of limitations from injury and a five-year absolute repose, with limited exceptions such as discovery of foreign objects.
- Common cases that qualify involve ignored red-flag symptoms, delayed diagnostics, or improper discharges, especially for time-critical conditions like stroke or heart attack.
- Building a successful claim heavily depends on thorough documentation, expert affidavits, and prompt action, as courts grant summary judgment more readily due to the high burden of proof.
Table of Contents
- What ER Malpractice Georgia Law Actually Requires
- Georgia’s Medical Malpractice Deadlines: What You Need to Know
- Common ER Mistakes That Cross Into Gross Negligence
- Who Can Be Held Liable for ER Malpractice
- Building Your Case: Evidence and the Expert Affidavit Rule
- How Georgia Courts Evaluate ER Malpractice Claims
- What to Do Right Now If You Suspect ER Malpractice
- How Jewkes Firm Evaluates ER Malpractice Claims
- The Honest Truth About ER Malpractice Cases in Georgia
- Get a Free Case Review From Jewkes Firm
- Key Statutes and Legal Resources for ER Malpractice Claims
- Sources
- FAQ
What ER Malpractice Georgia Law Actually Requires
Georgia carved out a special rule for emergency departments, and it changes everything about how these cases get built and won. Under § 51-1-29.5, a patient injured during “bona fide emergency medical care” cannot win a malpractice claim by showing ordinary carelessness. You have to show gross negligence, and you have to prove it with clear and convincing evidence, a tougher standard than the preponderance-of-the-evidence test used in typical injury cases.
The statute defines emergency medical care broadly, covering treatment given in a hospital emergency department to a patient with what appears to be a medical emergency, from the moment of triage until the patient is stabilized or admitted. That stabilization point matters enormously. Once a patient is admitted or medically stabilized, follow-up treatment often falls back under ordinary negligence rules, not the heightened ER standard. This is why so much litigation strategy in Georgia emergency room negligence cases centers on pinpointing exactly when “emergency care” ended.
The Georgia Supreme Court’s decision in Johnson v. Omondi shaped how lower courts apply this law. The court made clear that the gross-negligence standard governs any claim arising from care that qualifies as emergency treatment under the statute, regardless of how the plaintiff frames the allegations. Georgia courts have consistently read the statute to protect emergency physicians and staff from liability for judgment calls made under pressure, reserving liability for conduct that shows an utter disregard for patient safety.
That combination, gross negligence plus clear and convincing proof, filters out a large share of cases that would otherwise succeed as ordinary malpractice claims. A missed diagnosis alone rarely clears this bar. What tends to clear it: ignored red-flag symptoms, skipped standard-of-care tests with no documented reason, or a chart that shows no clinical reasoning at all behind a discharge decision. If you’re evaluating a potential emergency room negligence Georgia claim, understanding this distinction before you talk to an attorney will save you time and set realistic expectations from day one.
Georgia’s Medical Malpractice Deadlines: What You Need to Know
Two clocks run on every Georgia medical malpractice claim, and missing either one ends your case regardless of how strong the underlying facts are.
The general rule under O.C.G.A. § 9-3-71 gives you two years from the date of the injury to file suit. Georgia also imposes a five-year statute of repose, an absolute outer boundary that applies even if you did not discover the injury right away. Miss either deadline, and the courthouse door closes for good.
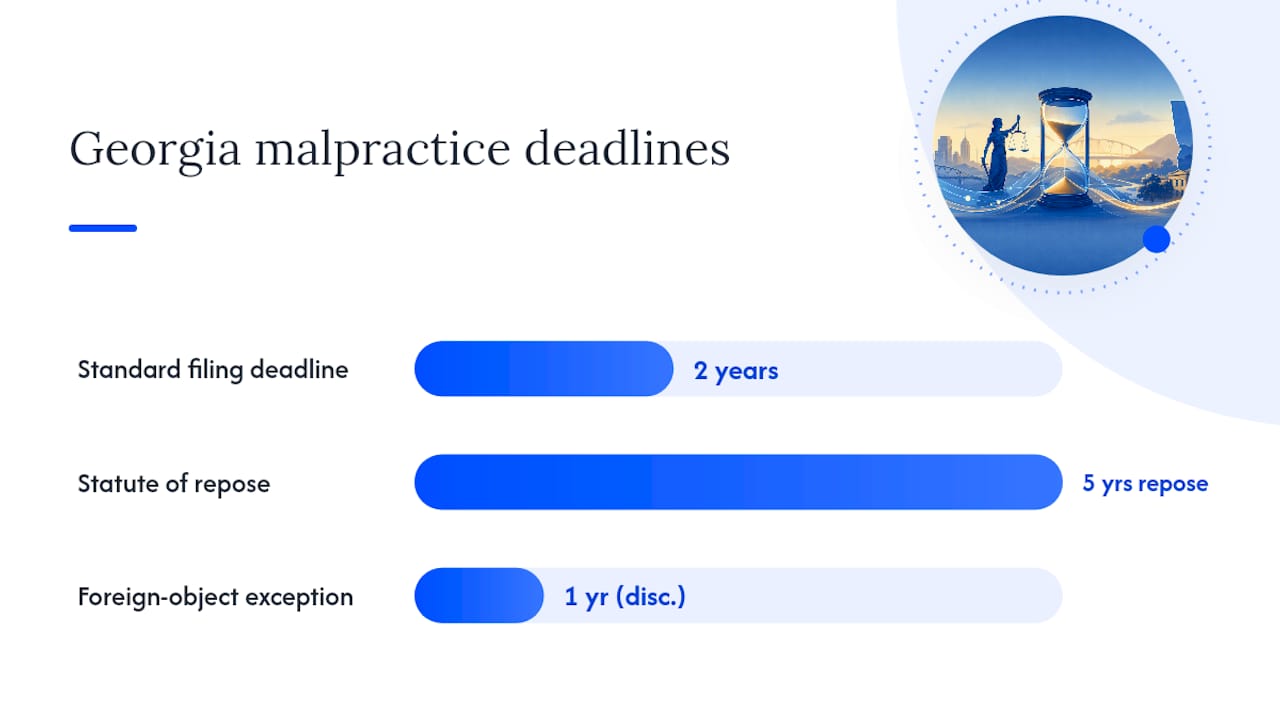
There’s one narrow but important exception. Under O.C.G.A. § 9-3-72, if a foreign object, a surgical sponge, a broken instrument tip, is left inside a patient’s body, the clock starts running from the date of discovery rather than the date of the original procedure, and the patient gets one year from that discovery date to file.
In practice, the “date of injury” question gets contested constantly in ER cases. A missed stroke diagnosis might not produce obvious harm for days or weeks, and pinning down exactly when the injury legally occurred often becomes its own fight. Discovery-related arguments can sometimes extend or toll a filing deadline, but Georgia courts apply these narrowly. Do not assume you have more time than the plain two-year rule suggests. If you suspect malpractice, treat the clock as already running and get a records request moving immediately.
Common ER Mistakes That Cross Into Gross Negligence
Not every bad outcome in an emergency department is malpractice, and under Georgia’s heightened standard, not every case of malpractice even clears the bar for a lawsuit. The gap between “the outcome was tragic” and “this was gross negligence” is where most ER malpractice Georgia cases either take shape or fall apart.
Certain patterns show up again and again in cases that do survive Georgia’s standard:
- Missed stroke: Classic stroke symptoms (facial droop, slurred speech, one-sided weakness) documented in triage notes but no imaging ordered within a clinically appropriate window.
- Missed heart attack: Chest pain and cardiac risk factors present, but no EKG performed or cardiac enzymes never drawn before discharge.
- Triage failures: A patient with objectively severe vital signs left waiting far longer than acuity protocols allow, with no documented reassessment.
- Improper discharge: A patient sent home with unresolved abnormal vitals, no follow-up instructions, and no documented reasoning for clearing them.
- Delayed imaging or labs: Orders written but never carried out, or results sitting unreviewed for hours during a time-sensitive presentation.
Time-sensitive conditions are exactly why these patterns matter so much. Stroke treatment has a narrow effective window, and research on diagnostic error shows how easily fast-moving ER environments produce missed or delayed diagnoses. Emergency departments handle a massive volume of visits nationally, according to CDC data, and that volume is precisely why triage and documentation discipline matter so much to how a case gets evaluated later.
The stabilization threshold is the hinge point in nearly every one of these examples. If a patient was still within the “bona fide emergency” window when the error occurred, the gross-negligence standard applies. If the patient had already been stabilized or admitted, ordinary negligence rules may govern instead, a distinction that can determine whether a case is viable at all.
Who Can Be Held Liable for ER Malpractice
An emergency room negligence Georgia claim rarely points at just one person. The attending physician carries direct liability for their own clinical decisions, but nurses, physician assistants, radiologists reading images remotely, and even the hospital itself can all end up as defendants depending on how the breakdown occurred.
Hospitals face liability two ways. Direct liability arises when the hospital’s own policies, staffing levels, or protocols caused or contributed to the harm, understaffing a triage desk during a known high-volume shift, for example. Vicarious liability arises when the hospital employs the negligent provider directly, making the hospital responsible for that employee’s conduct under respondeat superior principles. Many ER physicians, however, work as independent contractors through staffing agencies, which can shield the hospital from vicarious liability for that physician’s specific errors, even though the hospital may still face direct liability for its own systemic failures.
A typical case might name the treating physician, the hospital, and a staffing or nursing agency all at once, each theory resting on a different failure in the chain of care.
Building Your Case: Evidence and the Expert Affidavit Rule
Georgia does not let a malpractice complaint move forward on allegations alone. Under O.C.G.A. § 9-11-9.1, you must file an affidavit from a qualified expert alongside your complaint, and that affidavit has to specify at least one negligent act and the factual basis for that claim. File without one, or file a defective one, and the court can dismiss your case outright, sometimes before the substance of your claim is ever heard.
Meeting that requirement, and proving gross negligence later at trial, depends on documents that most patients never think to request until it’s too late.
- Triage notes and nursing acuity scores — these establish what symptoms were reported and how urgently staff classified the case.
- Time-stamped physician and nursing orders — these show exactly when tests were ordered versus when they were completed.
- Imaging and lab reports with timestamps — these prove whether time-sensitive diagnostics happened inside a clinically appropriate window.
- EKG strips and cardiac workup records — critical in missed heart attack claims specifically.
- Transfer and discharge records — these document the reasoning (or absence of reasoning) behind a decision to send a patient home or move them elsewhere.
Georgia malpractice attorneys who work these cases regularly emphasize obtaining timestamped triage logs and any available audiovisual footage early, because these records often decide whether care qualifies as a “bona fide emergency” under the statute in the first place, a determination that can decide the entire case before the facts of the treatment itself are even argued.
Pro Tip: Request your complete ER chart, not just a discharge summary, within days of the visit. Hospitals are required to maintain full timestamped records, and a complete chart showing gaps in testing or reassessment is often more persuasive than any single dramatic fact.
Charts that show a clear, documented thought process, differential diagnoses considered, tests ordered and reviewed, tend to protect the defense. Charts with unexplained gaps, no reassessment despite worsening vitals, no documented rationale for discharge, are what plaintiff’s counsel look for when building a gross-negligence argument. How medical records shape your injury claim covers this in more depth if you want to understand exactly what to request and why.
How Georgia Courts Evaluate ER Malpractice Claims
Section 51-1-29.5 doesn’t just raise the burden of proof, it also directs juries toward specific factors when they weigh the evidence: the patient’s medical history, whether a prior physician-patient relationship existed, the circumstances of the emergency itself, and the time pressures under which care was delivered. These factors give context to decisions that might look questionable in hindsight but were reasonable given what the provider knew in the moment.
Defense attorneys lean hard on summary judgment in these cases, arguing that even taking the plaintiff’s facts as true, no reasonable jury could find gross negligence by clear and convincing evidence. Because that standard is so demanding, Georgia courts grant summary judgment to ER defendants more readily than in ordinary negligence cases.
Plaintiffs survive that motion by pointing to specific, documented facts, not general characterizations of poor care. A chart showing stroke symptoms recorded at triage with no imaging ordered for hours creates a genuine factual dispute. A vague claim that “the doctor should have caught it sooner” usually does not. The strength of a case often comes down to whether the record itself, not just expert opinion, tells a clear story of disregarded warning signs.

What to Do Right Now If You Suspect ER Malpractice
Every week you wait costs you evidence, memory, and leverage. Georgia’s two-year clock does not pause for you to figure out what happened.
- Request the complete medical record immediately, including triage notes, nursing flowsheets, and time-stamped orders, not just the discharge summary.
- Photograph visible injuries and any physical evidence connected to the harm, such as pressure sores, surgical complications, or medication packaging.
- Write down names of every nurse, physician, and staff member you interacted with, along with the approximate time of each interaction, while your memory is fresh.
- Keep every bill, receipt, and record of lost income tied to the harm, since these documents anchor your damages claim later.
- Contact a Georgia malpractice attorney early, bringing your records request, photos, and a written timeline of events to the first consultation.
The realistic sequence after that first call typically runs: records collection, expert review to determine whether the facts meet the gross-negligence standard, preparation of the § 9-11-9.1 affidavit, then filing. Each step depends on the one before it, which is exactly why early action protects your options instead of narrowing them. The medical malpractice checklist walks through this preservation process in more detail if you want a reference to follow while you gather documents.
How Jewkes Firm Evaluates ER Malpractice Claims
Medical malpractice practice often focuses on emergency department errors where Georgia’s gross-negligence standard controls the outcome. Many firms offer free consultations and contingency fee arrangements, meaning clients owe nothing unless the firm recovers for them.
Evaluating an ER claim starts with securing the full medical record before anything gets lost or altered, then matching those records against experts who can speak specifically to Georgia’s statutory gross-negligence definition, not just general standard-of-care deviations. At intake, expect to walk through your timeline, hand over whatever records you already have, and get a candid assessment of whether your facts can realistically meet Georgia’s heightened bar.
The Honest Truth About ER Malpractice Cases in Georgia
Most bad outcomes in an emergency room, even painful, life-altering ones, simply do not meet Georgia’s gross-negligence standard, and pretending otherwise does no one any favors. What separates a viable claim from a dead end is almost always the documentation: a chart with unexplained gaps, ignored red flags, or no clinical reasoning behind a discharge. Preserve your records fast, and get an experienced set of eyes on them before evidence disappears. Acting within weeks, not months, is what actually protects your options here.
— Ali
Get a Free Case Review From Jewkes Firm
Jewkes Firm gives Georgia patients something most people don’t realize they’re entitled to after a bad ER outcome: a straight, no-cost assessment of whether their case can actually clear Georgia’s gross-negligence bar before they spend months chasing a claim that was never viable. That evaluation covers a full review of your emergency room records, an honest read on timing and documentation gaps, and early engagement with medical experts who understand how to frame a deviation under the statutory test, not just general standards of care.

There’s no fee unless the firm recovers for you, and the first consultation costs nothing. Bring whatever records you already have, along with your own timeline of what happened and when. From there, the firm handles records requests, expert vetting, the required affidavit, and litigation if the facts support it. Emergency room cases sit alongside the firm’s broader medical malpractice and related practice areas, covering everything from birth injuries to wrongful death claims across South Atlanta and the surrounding Georgia counties. If you suspect an ER error caused serious harm, call for your free case review before the two-year clock runs any further.
Key Statutes and Legal Resources for ER Malpractice Claims
Review the controlling law directly: the gross-negligence standard under § 51-1-29.5, the filing deadlines in § 9-3-71 and § 9-3-72, the Johnson v. Omondi opinion, and a plain-language overview from Nolo.
This article is general information, not a substitute for advice from a qualified lawyer. Consult a qualified legal professional about your own circumstances before acting on anything here.
Sources
- § 51-1-29.5 – Definitions; limitation on health care liability claim to gross negligence in emergency medical care; factors for jury consideration
- Section 9-3-71 – General limitation (Georgia Code)
- Johnson v. Omondi (Georgia Supreme Court opinion)
- Georgia law commentary on affidavit requirement and malpractice procedure
- Georgia medical malpractice lawsuit requirements — Nolo
FAQ
How often does an ER doctor get sued?
ER physicians face malpractice claims less often than surgeons or obstetricians, largely because Georgia’s gross-negligence standard under § 51-1-29.5 screens out a large share of potential claims before they’re ever filed.
What is the largest malpractice settlement in Georgia?
Georgia does not publish a single verified record for the largest medical malpractice settlement, and settlement amounts vary enormously by injury severity, liability strength, and whether a case settles or goes to verdict; a Georgia malpractice attorney can give you a realistic range based on your specific facts.
What kind of negligence state is Georgia?
Georgia is a modified comparative negligence state for most injury claims, but ER malpractice claims specifically require proof of gross negligence by clear and convincing evidence under § 51-1-29.5, a materially higher bar than ordinary comparative negligence rules.
What’s the average malpractice settlement amount?
There is no single reliable average, since Georgia malpractice settlements depend heavily on injury severity, available insurance coverage, and how clearly the medical record supports gross negligence; Jewkes Firm evaluates each case individually during a free consultation rather than relying on generic averages.
Do I need an expert affidavit to sue for ER malpractice in Georgia?
Yes. Under O.C.G.A. § 9-11-9.1, Georgia requires an expert affidavit filed alongside your complaint, and a missing or defective affidavit can get your case dismissed regardless of its underlying merits.
